How Bastjänstgöring Works for Doctors in Sweden
BT in Sweden, or bastjänstgöring, is the common introductory part of the newer Swedish specialist-training system. It takes place at the beginning of specialiseringstjänstgöring (ST), after medical qualification and ordinarily after Swedish medical licensure. National rules require at least six months of BT, including at least three months in primary care and three months in acute healthcare, but Socialstyrelsen explains that about one year is normally needed to achieve all BT objectives.
BT is not simply time served and it is not the same as the older Swedish allmäntjänstgöring (AT). A doctor needs an individual training programme, supervision, documented assessments and evidence that all 18 national BT objectives have been met. This guide explains who needs BT, how it is organised, what can be credited, how approval works and how BT connects to the rest of ST.

BT in Sweden at a glance
Bastjänstgöring was introduced into the new ST framework on 1 July 2021. Its purpose is to give doctors in every future specialty a shared clinical foundation and a structured introduction to Swedish healthcare. The doctor completing it is called a BT-läkare.
The common foundation is deliberately broad. It strengthens independent clinical decision-making and first-line care while introducing the doctor to Swedish rules, decision support, documentation and healthcare organisation. Because doctors enter BT with different educational and professional backgrounds, the individual programme must respond to actual learning needs rather than assume identical preparation.
| Question | National position |
|---|---|
| Where does BT sit? | At the beginning of the newer ST system. BT time is included in the minimum duration of ST; it is not added on top. |
| Minimum duration | Six months at full-time equivalence, provided every time and competence requirement is met. |
| Normal planning assumption | About 12 months for a doctor without credited service. Regional programmes commonly advertise 12-month arrangements. |
| Mandatory clinical settings | At least three months in primary care and at least three months in acute healthcare. |
| Possible formats | A separate, standalone BT post or BT integrated into an employment covering the wider ST pathway. |
| How completion is judged | Through documented competence assessments against the national objectives, not by elapsed time alone. |
| Final national step | The doctor applies to Socialstyrelsen for an intyg om godkänd bastjänstgöring, a certificate of approved BT. |
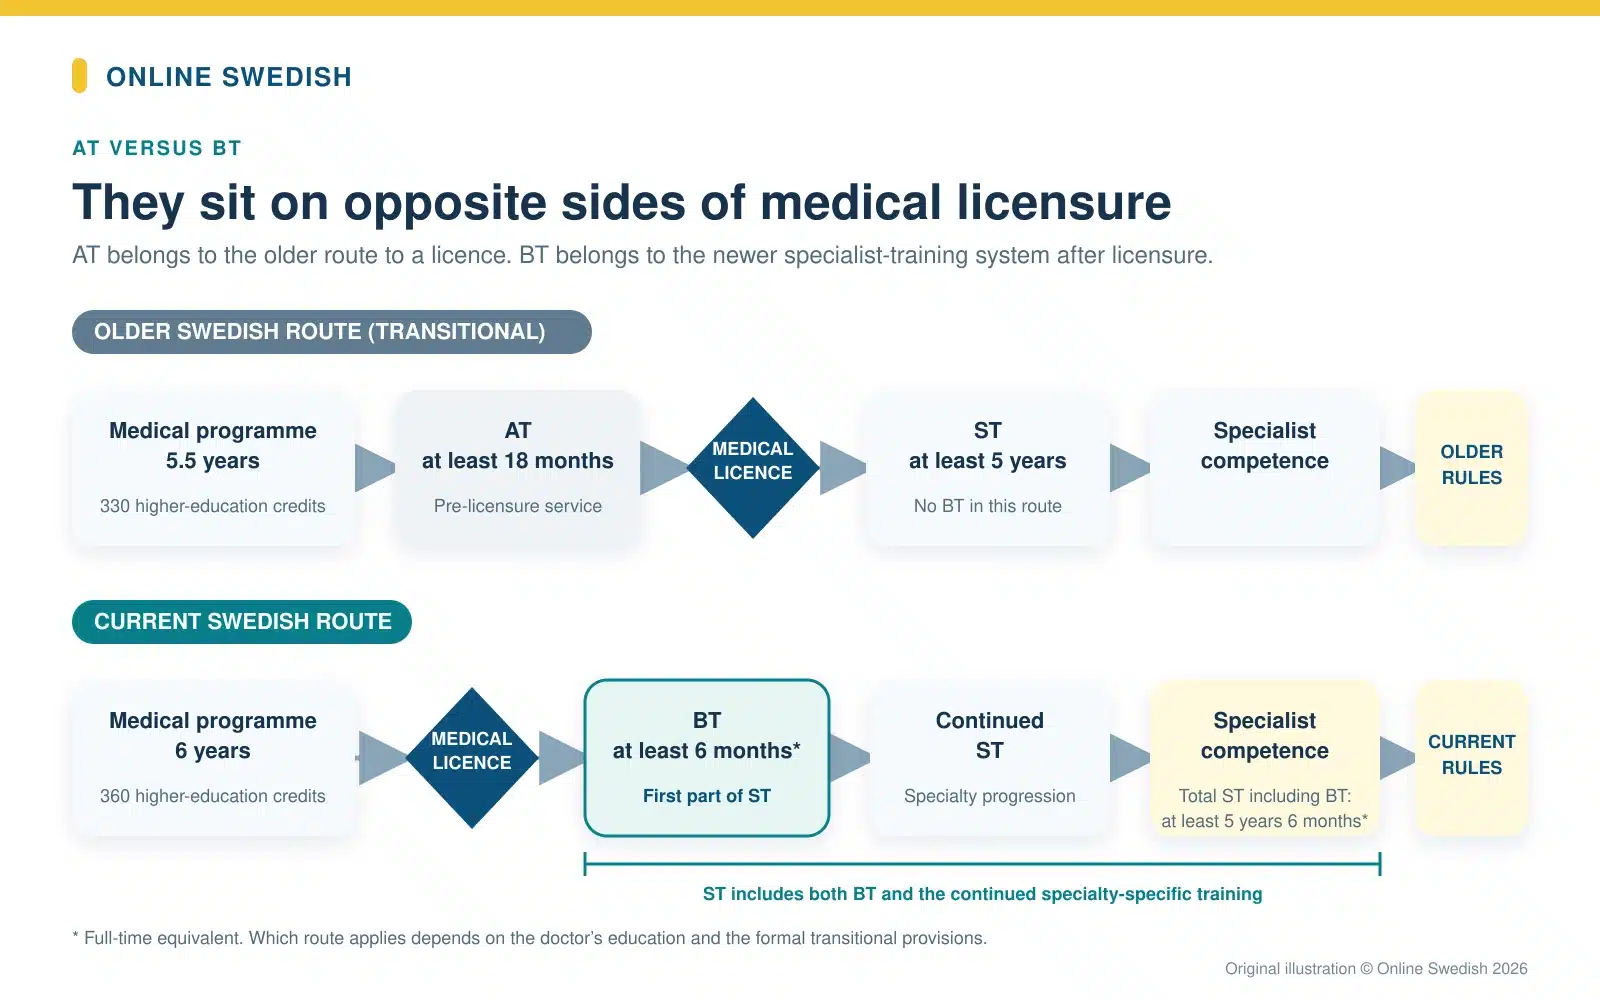
AT and BT therefore solve different problems. AT belongs to the older route and, for doctors covered by that system, precedes Swedish licensure. BT belongs to the newer specialist pathway and follows licensure in the ordinary sequence. Doctors uncertain about the boundary should use the dedicated comparison of Swedish AT and BT for doctors.
Who needs bastjänstgöring?
The decisive issue is which specialist-training rules apply to the doctor. It is not safe to decide from nationality, country of graduation or the date on a licence alone.
Under the transitional provisions, doctors who completed Swedish AT, and doctors who began but did not complete ST before 1 July 2021, may still have their specialist application assessed under the older SOSFS 2015:8 rules. That older framework has a five-year minimum ST duration and no BT. Doctors outside those transitional groups use the newer HSLF-FS 2021:8 framework, in which ST lasts at least five years and six months and begins with BT.
| Doctor’s situation | Likely BT position | What to verify |
|---|---|---|
| Licensed after Sweden’s newer six-year medical degree | BT is normally the first part of ST. | Employer’s BT/ST format and individual training programme. |
| EU/EEA-trained doctor licensed in Sweden without Swedish AT | BT normally applies when entering Swedish ST under the new rules. | Any earlier ST service that could place the doctor within a transitional provision. |
| Non-EU/EEA-trained doctor who has obtained Swedish licensure | BT normally applies when beginning Swedish ST under HSLF-FS 2021:8. | Whether documented earlier work can be credited and how BT objectives will be assessed. |
| UK-trained doctor | The post-Brexit licensing route comes first; BT then depends on the Swedish ST framework that applies. | The individual licensing decision and any recognised prior specialist training. |
| Doctor who completed Swedish AT | The older ST rules remain available; BT is not required under that route. | Evidence of completed Swedish AT and the intended regulatory framework. |
| Doctor who began ST before 1 July 2021 | The older rules may remain available even if ST was interrupted. | Dates, documentation and whether the earlier service legally counts as begun ST. |
| Already recognised specialist from the EU/EEA | Direct recognition of the specialist qualification is a different route and may avoid ordinary Swedish BT. | Socialstyrelsen’s decision on recognition rather than assumptions based on employment title. |
| Specialist trained in a third country | Special rules may require Swedish ST service and fulfilment of both BT and specialty objectives. | Which service can be credited and the requirements stated in the individual case. |
BT only has to be completed once. A doctor who later trains in an additional specialty does not repeat approved BT, although the new specialty can require further service and competence evidence.
Eligibility before applying for BT
BT is designed for a licensed doctor entering specialisation. Regional employers therefore normally expect a Swedish läkarlegitimation by the date stated in the vacancy, as well as sufficient Swedish for safe independent clinical work under supervision. A work permit or residence right is a separate immigration question: medical licensure does not create a right to work, and a work permit does not replace professional authorisation.
Doctors waiting for licensure may be able to work in other medical roles when the legal and employer conditions are met. However, an underläkare job is not automatically a BT post. The guide to working as an underläkare in Sweden explains that employment route separately.
Before applying, confirm these points:
- you hold Swedish medical licensure, or will hold it by the employer’s stated deadline;
- the post is formally organised under HSLF-FS 2021:8;
- the employer can provide the required primary-care and acute-care service;
- a main responsible manager, study director and qualified supervisors are available;
- the programme uses documented workplace assessments and can arrange the final external assessment;
- any claimed earlier service has been reviewed rather than merely mentioned in an application; and
- the employment and immigration conditions permit you to complete all planned placements.
Swedish ability matters beyond licensing evidence. BT objectives include safe documentation, oral and written explanation, teamwork, patient participation, certificates and communication across services. Employers may evaluate professional Swedish during recruitment even after a doctor has met Socialstyrelsen’s licensing-language requirement.
How long BT takes
The legal minimum is six months of full-time-equivalent service. That minimum follows from the requirement for at least three months in primary care and at least three months in acute healthcare. It is not a promise that a programme, or an individual doctor, will finish in six months.
Socialstyrelsen describes about one year as a common period for reaching the objectives. The 2021 learning-objective publication likewise refers to a 12-month norm for an average doctor without credits. Many regional programmes therefore plan 12 months, but the exact structure is set locally and adapted to the doctor’s development.
Time and competence must both be complete
BT is competence-based within minimum time rules. Completing a calendar period is insufficient if an objective has not been demonstrated. Conversely, previous experience does not remove the need for assessors to verify competence. If the objectives are not met at the planned end date, the training may need to continue.
Part-time BT is possible, but the period must be extended until it equals the required full-time service. The regulations allow annual leave and time off earned through on-call work to be included in ST service time. Parental leave does not count as service time and can extend the calendar duration.
How BT fits inside the total ST time
Under HSLF-FS 2021:8, the complete ST must equal at least five years and six months at full time, including BT. If BT takes 12 months, the remaining ST service must normally be at least four years and six months. A six-month BT does not normally reduce the whole pathway below five years and six months.
The rest of ST may begin while the doctor is still completing BT. Socialstyrelsen’s general advice is that, when the two overlap in this way, the training should be planned so the doctor can apply for approved BT within the first two full-time years. Activities undertaken during BT can sometimes support later specialty objectives, but only when the supervision and evidence also satisfy the rules for those objectives.
Rotations and competence objectives
The national regulation fixes two placement requirements: at least three months in primary care and at least three months in acute healthcare. Acute healthcare must give the doctor opportunities to manage acute conditions across several diagnostic areas. This does not necessarily mean that every region uses the same departments or that all acute service occurs in one emergency department.
The general advice says BT should normally use no more than four service locations and should favour longer coherent periods. These are planning recommendations, while the time in primary and acute care is a binding requirement.
There are 18 national BT objectives. They cover more than acute and non-acute clinical decision-making. The broad competence areas include:
- acute, common non-acute and psychiatric conditions;
- Swedish healthcare law, organisation and collaboration with other public actors;
- structured patient documentation and safe communication;
- quality improvement, scientific thinking and ethics;
- respectful patient encounters, teamwork, leadership and patient participation;
- children’s needs and rights, hygiene, infection control and health promotion;
- safe medication treatment;
- insurance-medicine certificates; and
- palliative care, death certificates and cause-of-death certificates.
The BT objectives describe competence that must be demonstrated rather than a single national course package. Supervised clinical work is central, while an individual programme can add courses, other internal or external activities and self-study where needed. For every objective claimed in the final application, the documentation must identify both the learning activities and how attainment was checked.
Psychiatric competence is therefore mandatory, but the national regulation does not prescribe a fixed number of psychiatry months in the way it prescribes primary-care and acute-care time. The local programme must still create a credible way to teach and assess the psychiatric objectives. For a detailed map of placements, all 18 objectives and suitable assessment evidence, use the guide to what doctors do during bastjänstgöring.
Standalone or integrated BT
Employers can organise BT as a separate post or as the first phase of a broader ST employment. Both routes must meet the same national BT objectives and assessment rules.
| Decision factor | Standalone BT | Integrated BT/ST |
|---|---|---|
| Employment scope | Normally a time-limited post covering BT. | BT is built into employment intended to continue into a named specialty. |
| Specialty commitment | Allows a later ST decision after completing the common foundation. | Requires an earlier specialty and employer decision. |
| Continuity | The doctor usually applies separately for a later ST post. | Can provide continuity of employment, training plan and specialty supervision. |
| Main risk | There is no automatic ST post after BT. | Changing specialty or employer can require a new employment decision and revised plan. |
| Best fit | Doctors seeking a broad entry route or still choosing a specialty. | Doctors with a clear specialty choice and a suitable long-term employer. |
The better format depends on the actual contract, supervision, rotation access, specialty plans and location—not on the label alone. Compare the implications in the dedicated guide to fristående BT and integrated BT before accepting an offer.
Supervision, assessment and the training plan
Every BT doctor must have an individual training programme based on the national objectives. It should cover the required clinical service, additional educational activities, planned supervision and assessments, and time for self-study. It must be reviewed regularly and revised when the doctor’s development or programme conditions change.
Who is responsible for BT?
- The healthcare provider must create the conditions for consistent, high-quality specialist training and provide access to a study director, supervisors and clinical instructors.
- The main responsible manager, normally a service manager at one of the placements or a person with an appropriate organisational role, carries overall responsibility for BT, the training programme and appointment of the principal supervisor.
- The study director coordinates internal and external education and supports the organisation.
- Placement supervisors guide and assess the doctor during each part of BT.
- The principal supervisor follows development across the whole BT and combines information from the different placements.
- An external assessor participates in the final overall judgement of whether the BT objectives have been achieved.
A BT supervisor must be a licensed doctor, be either a specialist or an ST doctor, and have completed supervisor training. The external assessor must be a licensed specialist with competence in assessment and must not have worked with the BT doctor at the same care unit or otherwise participated in that doctor’s BT.
What good assessment looks like
Competence must be assessed continuously against both the national objectives and the individual programme, and the assessments must be documented. Each service period ends with an overall assessment. Before the final competence certificate is signed, the principal supervisor and external assessor make a combined judgement using the accumulated evidence.
BT therefore does not end with one national written or practical examination comparable to the former AT examination. Approval is built from repeated documented workplace assessments, the combined assessment after each service period and the final review by the principal supervisor and external assessor. Regional programmes may use tools such as mini-CEX, DOPS, case-based discussion (CBD) and multi-source or 360-degree feedback. These are examples, not nationally mandatory brands: the regulation requires the provider to establish suitable methods and routines.
If an assessment shows that the doctor may not reach the objectives, the general advice calls for an action plan. It can adjust the individual programme, improve the provider’s educational support or clarify what the doctor must do. A documented improvement plan is more useful than waiting until the final weeks to discover missing evidence.
Assessment of the individual doctor is separate from quality assurance of the programme. The provider must systematically review whether BT and ST meet the regulatory requirements and arrange evaluation by an external actor without organisational links to the provider. Socialstyrelsen’s general advice is that the external programme review should normally occur every five years.
Finding and applying for a BT position
Sweden has no single national BT matching system. Regions and other healthcare providers organise and advertise their own posts. Recruitment dates, the number of posts, employment form, programme length and whether BT is standalone or integrated can therefore differ substantially.
Current regional information illustrates that variation. Stockholm describes both 12-month standalone BT and integrated BT/ST. Västra Götalandsregionen advertises regional standalone posts as well as ST posts with integrated BT. Region Skåne publishes its own recruitment rounds and is expanding its model. These examples are useful for planning, but they are not national deadlines and they can change.
What employers may assess
Vacancy-specific criteria control the application. Employers may assess the Swedish licence, professional Swedish, clinical experience, references, motivation for the region, teamwork, patient-safety judgement and the ability to learn from supervision. Competition and waiting time vary by region and recruitment round; there is no reliable national promise that every licensed doctor will receive a BT post within a fixed period.
A practical application file may include:
- a Swedish-style medical CV and tailored personal letter;
- proof of Swedish licensure or evidence that it will be issued by the required date;
- medical degree and relevant employment certificates;
- references who can describe recent clinical work;
- documents supporting any earlier service you want the programme to consider; and
- clear information about work authorisation when relevant.
For vacancy channels, interview preparation, regional timing and a step-by-step application strategy, continue with the guide to applications and competition for BT posts.
Crediting earlier medical work
Previous work can matter, but credit is never created merely by listing experience on a CV. The responsible people in the Swedish BT programme must assess relevance, time and competence, and Socialstyrelsen can later ask for clarification or reject service that does not satisfy the rules.
Service performed after the medical degree but before Swedish licensure, or before equivalent authorisation in another country, can in some circumstances contribute up to six months. It must have been medical work under supervision and relevant to BT. This possibility can include work in primary care and acute healthcare. It does not mean that any pre-licensure underläkare employment automatically becomes BT.
Foreign service after authorisation in the country of work may also be credited within the wider ST limits when it was supervised, documented by a service manager or equivalent, and judged by a Swedish supervisor to meet relevant objectives. The rules allow up to four years and six months of qualifying foreign service to be considered in ST overall, but that ceiling is not a guarantee and does not remove the requirement to demonstrate every BT objective.
A doctoral degree can reduce the countable service time in ST by six months when the regulatory conditions are met, but it cannot reduce the BT component itself. Doctors should keep certified service descriptions showing dates, percentage of full-time work, clinical content, supervision and the authorising person’s role. The separate article on whether earlier underläkare work counts toward BT or ST will examine this evidence question in depth.
Applying to Socialstyrelsen for approved BT
The doctor—not the employer—submits the application for an intyg om godkänd bastjänstgöring. Before submitting, check that the official forms agree on names, dates, percentages, service locations and objectives.
The three core BT certificates
- Intyg om delmål i bastjänstgöringen: identifies the BT objectives, the educational activities used and how achievement was checked; the assessing supervisor signs it.
- Intyg om fullgjord bastjänstgöring: records service locations, periods, scope and which parts were completed in primary care and acute healthcare; the main responsible manager signs it.
- Intyg om uppnådd baskompetens: confirms the final combined competence judgement; the principal supervisor and external assessor normally sign it.
Socialstyrelsen’s e-service accepts the documents in PDF form. A paper route is available when the e-service cannot be used, but the instructions for originals, copies and payment differ, so use the current application page rather than an old checklist.
Socialstyrelsen currently lists the application fee for approved BT as SEK 1,890. Fees can change. Confirm the amount and payment method immediately before submitting, particularly if applying on paper.
Approval is separate from employer sign-off
The employer and supervisors document service and competence, but Socialstyrelsen issues the national approved-BT certificate. Socialstyrelsen does not normally give advance approval of an individual BT arrangement. That makes it important to solve unclear rotations, missing assessments and credit questions while the evidence and responsible signatories are still available.
What happens after BT?
Approved BT is a milestone within ST, not a specialist certificate. The doctor continues the specialty-specific parts of training until the complete time, activity and competence requirements are met. A standalone BT doctor must obtain a suitable ST post; a doctor in integrated BT/ST normally continues under the wider employment and revised training programme.
The approved BT certificate will later form part of the evidence for specialist recognition. A doctor who has already started some later ST activities while finishing BT should make sure the programme clearly records which supervision standard and objectives each activity satisfies.
BT does not have to be repeated for a second specialty. However, service credited from one specialty to another is a separate question, and each new specialist application must meet the applicable specialty objectives and total-time rules.
Watch doctors discuss BT
Formal rules explain what must happen; first-hand accounts show how doctors experience the transition. Watch Doctors Going to Sweden, Part 2: AT vs BT, Socialstyrelsen, and Real Stories from Foreign Doctors for a practical discussion of AT, BT and international doctors’ routes.
Doctors Going to Sweden, Part 2: AT versus BT and experiences of foreign-trained doctors.
For complementary experiences, watch Part 4: Work as a doctor in northern Sweden, which includes discussion of early clinical work and BT, and Part 7: Survival Guide After the Licence, which focuses on the professional stage after Swedish licensure.
BT planning checklist
Use this sequence to keep licensing, employment and training evidence separate:
- Confirm your regulatory route. Decide whether HSLF-FS 2021:8 or a transitional older rule applies, using documents rather than memory.
- Obtain Swedish licensure. Treat work authorisation as a separate immigration task.
- Choose a format deliberately. Compare standalone BT with integrated BT/ST, including what happens after the BT phase.
- Audit the programme. Check rotation access, supervisors, study director, external assessment and documentation routines.
- Present earlier service early. Submit detailed certificates before the programme is fixed and ask how credit will be decided.
- Agree an individual training programme. Map every BT objective, service period, learning activity and assessment.
- Save evidence continuously. Keep signed assessments and current copies of the plan after every placement.
- Act on gaps promptly. Request a written action plan when progression or supervision is unclear.
- Review the Socialstyrelsen forms before the final month. Identify missing signatories while they are still accessible.
- Apply for approved BT. Use the current e-service instructions and verify the fee at submission.
- Update the wider ST plan. Record what continues, what can support specialty objectives and the minimum remaining time.
Frequently asked questions
Can I start BT before receiving Swedish medical licensure?
BT belongs to post-licensure specialist training, so a formal BT post is ordinarily entered as a licensed doctor. A limited exception allows certain supervised medical service completed after the degree but before Swedish or foreign authorisation to be credited, up to six months. Credit is individual and is not the same as automatic approval of the earlier job as BT.
Do EU/EEA doctors need BT in Sweden?
An EU/EEA doctor who receives Swedish licensure and enters Swedish specialist training under HSLF-FS 2021:8 normally needs BT. A doctor with completed Swedish AT, qualifying pre-July-2021 ST or an already recognised specialist qualification may follow a different route. Country of graduation alone does not decide the answer.
Is BT always 12 months?
No. The national minimum is six full-time-equivalent months, while Socialstyrelsen says about one year is commonly needed to reach the objectives. Regional programmes often plan 12 months. BT can take longer when it is part time, competence evidence is incomplete or absence extends the service period.
Must BT include a fixed psychiatry rotation?
Psychiatric competence is mandatory under objective BT2, including acute psychiatric assessment and suicide-risk assessment. The national regulation, however, fixes minimum service time only for primary care and acute healthcare; it does not prescribe a national minimum number of psychiatry months. The provider must still arrange credible learning and assessment of BT2.
Can I change hospital or region during BT?
The national regulation does not state that a doctor may change BT provider only once. A change is nevertheless not automatic: it requires a new employment decision and a receiving organisation willing to plan the remaining BT and evaluate earlier evidence. Before leaving, obtain signed service periods, objective certificates, documented assessments and the latest training programme. Ask the new responsible manager in writing what will be accepted.
Does a foreign internship or previous clinical work replace BT?
Not automatically. Relevant supervised service can sometimes be credited if it meets the regulatory conditions and can be mapped to BT time and objectives. The Swedish programme’s responsible people assess the evidence, and Socialstyrelsen reviews the final application. A foreign programme with the same duration but different content may leave objectives that must still be completed in Sweden.
Your next step in Swedish specialist training
Start by identifying the regulations that apply to you, then evaluate the actual BT programme rather than relying on its title. A safe arrangement provides the required clinical settings, an individual plan, qualified supervision, repeated documented assessment and a clear route to the final Socialstyrelsen forms. When earlier work, a provider change or a transitional rule affects your case, obtain decisions and evidence in writing before assuming that time will count.
Official sources
- Socialstyrelsen: Complete specialist training with introductory BT and ST
- Socialstyrelsen: Consolidated HSLF-FS 2021:8 regulations for doctors’ specialist training
- Socialstyrelsen: 2021 learning objectives for BT and ST
- Socialstyrelsen: Submit and pay for a BT or specialist application
- Sveriges riksdag: Patientsäkerhetsförordning (2010:1369)
- Region Stockholm: BT programme formats
- Västra Götalandsregionen: Bastjänstgöring recruitment and formats
- Västra Götalandsregionen: Workplace-based assessment templates
- Region Skåne: BT organisation and recruitment